Global Channels
Why Institutional Partnerships Matter for Korea’s Medical Tourism Channels
Insurance, travel, and employee-benefit partnerships create different patient pathways. Their value depends on eligibility, handoffs, capacity, and economics.
When paid acquisition becomes more expensive, institutions with established customer relationships become more valuable distribution partners. For Korean hospitals serving international patients, that makes insurers, travel companies, and employers strategically relevant.
The distinction is between a commercial rationale and a documented market trend. Rising acquisition costs can strengthen the case for partnerships without proving that institutional referrals are expanding across Korea’s medical-tourism market.
An existing audience changes the acquisition equation
An institution already has reasons to communicate with its members, customers, or employees. A hospital partnership can introduce a medical-service pathway within those relationships, reducing the need to establish every patient connection through advertising.
That access has value only when the audience has a relevant need. A large membership base says little about willingness to travel, treatment eligibility, affordability, or readiness to contact a Korean provider.
Institutional access also carries costs. Partner onboarding, translated materials, staff training, referral administration, and account management can absorb resources before a patient arrives. A lower advertising bill does not necessarily mean a lower total acquisition cost.
KHIDI and Medical Korea provide official context for Korea’s international patient sector and its institutional framework. Those resources should inform market assessment, while claims about a particular channel’s growth require evidence specific to that channel.
The strategic question is therefore precise: can a partner create repeatable access to relevant patients at an acceptable total cost? Counting signed agreements cannot answer it.
Insurance, travel, and employee benefits activate different demand
These institutions should not be treated as interchangeable referral sources. They reach people at different moments, influence different decisions, and participate in different payment arrangements.
An insurance pathway may begin with a coverage inquiry or a request for assistance. Before a hospital presents that pathway as financially accessible, the parties need to establish what the particular policy covers and how payment would work.
A travel company reaches people who are considering or arranging a journey. Its contribution may be destination information and travel coordination, while clinical suitability and the time needed for care remain matters for the hospital to assess.
An employer or benefits administrator reaches a defined employee population. The offer might involve navigation support, an employer-funded benefit, or access to a service paid for by the employee. These arrangements create different expectations and administrative obligations.
Table: Different institutions create different patient pathways
| Partner type | Potential demand trigger | Payment issue to establish | Essential handoff |
|---|---|---|---|
| Insurer | Coverage inquiry or assistance request | Policy eligibility, authorization, and payment responsibility | Coverage context to hospital assessment |
| Travel company | Destination planning or an existing trip | Separation of travel charges and medical fees | Travel inquiry to clinical consultation |
| Employer or benefits administrator | Benefit communication or an employee request | Employer contribution and employee responsibility | Benefit eligibility to private patient contact |
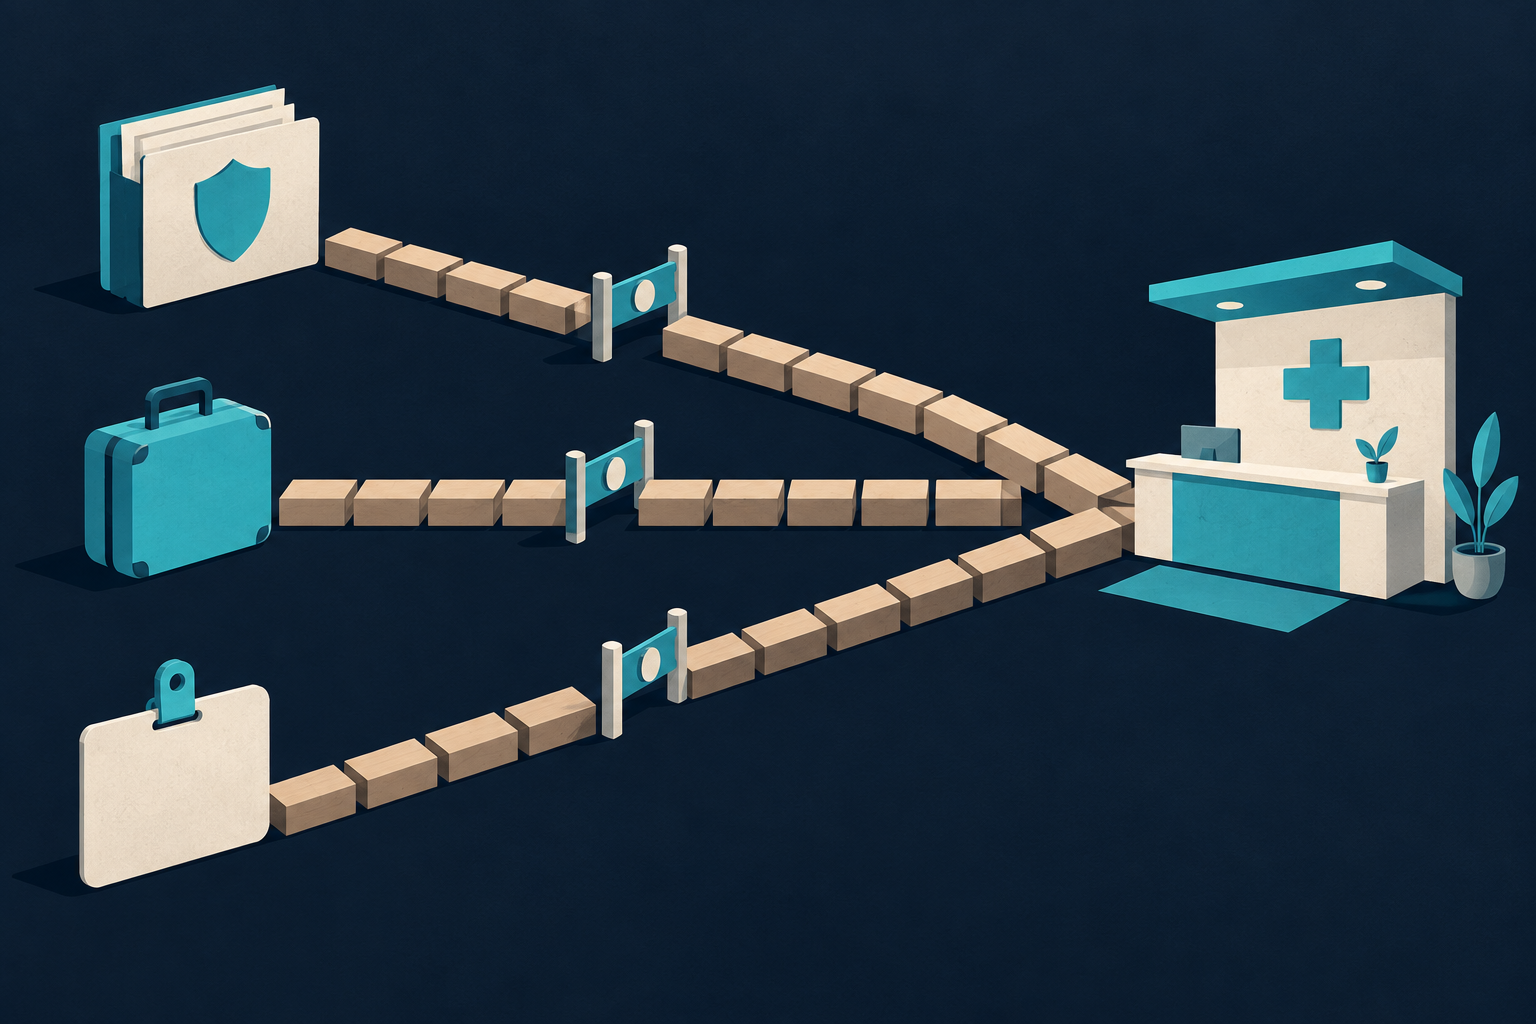
A shared brochure cannot resolve these differences. Each pathway needs its own explanation of eligibility, the next step, financial responsibility, and the decisions that remain subject to clinical assessment.
For hospitals building an international patient acquisition program, partner selection should follow those operational differences. The useful partner is one whose audience and referral process fit the hospital’s services and capacity.
Group acquisition means shared eligibility, not shared arrival dates
Institutional distribution is often confused with bringing a group of patients to a hospital together. Its more durable feature is repeated access to people who share an eligibility condition, such as policy membership or participation in an employee benefit.
Those individuals may inquire and travel at different times. The institution provides a recurring route into the hospital’s consultation process, rather than a single departure date or a coordinated booking event.
This distinction changes program design. A one-time promotion depends on immediate response. A continuing partnership needs information that remains available, a clear place to ask questions, and a reliable way to confirm whether the offer applies.
Consider a hypothetical employer partnership. An initial announcement may generate interest, but later inquiries could arise when employees revisit their benefits information. If the referral contact has changed or the terms are unclear, the earlier communication loses practical value.
Recurring access is therefore an operating capability. It depends on maintaining accurate materials, updating partner staff, and preserving the path from eligibility inquiry to hospital consultation.
It also requires separating shared eligibility from individual medical decisions. Membership in an institutional program does not establish suitability for a procedure, and a commercial partner should not make that determination.
Reliability comes from handoffs and hospital capacity
A contract creates a relationship; it does not create a functioning patient pathway. Stability depends on whether the institution can explain the offer consistently and whether the hospital can take over the conversation without losing essential context.
A weak handoff makes patients repeat information or leaves them uncertain about whom to contact. A stronger handoff identifies the referral source, the purpose of the inquiry, the appropriate hospital contact, and the information needed for the next decision.
Information sharing needs particular care. Korea’s National Law Information Center provides the relevant statutory texts on foreign patient attraction and personal information protection. Specific arrangements require review against the applicable rules, including the parties’ roles and proposed data flows.
Operationally, the parties should establish what information is necessary and how it will be handled before referrals begin. Commercial coordination should not lead to unnecessary circulation of sensitive patient details.
Hospital capacity is equally decisive. A partner may generate inquiries during periods when multilingual consultation, appointment availability, or follow-up coordination is constrained. Demand then becomes a service bottleneck rather than productive growth.
This is where hospital management and operational consulting connects to channel strategy. Referral commitments need to match staffing, scheduling, language support, and financial administration, so that the hospital can sustain the promised access process.
The practical test is whether the pathway works repeatedly under ordinary operating conditions. A partnership that depends on constant intervention from a single coordinator is vulnerable even when its initial patient feedback is positive.
Measure the full pathway, including dependence
Inquiry volume is an early signal, not a complete measure of commercial value. Hospitals need to understand whether eligible inquiries progress to consultation and attendance, and what resources are consumed along the way.
Different partners may contribute at different stages. A travel partner might introduce patients who already intend to visit Korea, while an employer program might reach people much earlier in their decision process. Direct conversion comparisons need that context.
Table: A broader framework for assessing partnership performance
| Dimension | What to examine | What it helps reveal |
|---|---|---|
| Patient progression | Eligible inquiries, consultations, and attendance | Whether access becomes actual service use |
| Operating burden | Coordination, interpretation, and administrative work | The resources required to sustain the channel |
| Financial performance | Collected revenue, attributable costs, and settlement delays | Whether activity produces an acceptable contribution |
| Service continuity | Handoff failures, unresolved questions, and capacity constraints | Where the patient pathway breaks down |
| Partner concentration | Dependence on a particular institution | Exposure to changes outside the hospital’s control |
Settlement deserves separate attention. The responsible payer, invoicing process, disputed charges, and payment timing can materially affect the value of a referral relationship. Booked activity and collected revenue should remain distinct in management reporting.
Concentration also changes the interpretation of success. A productive institutional relationship can become a vulnerability if the hospital relies heavily on that institution’s communications, personnel, or benefit policy. Growth should be assessed alongside that dependence.
Institutional partnerships offer a way to make international patient access more repeatable. Their strategic value rests on relevant audiences, clear eligibility, dependable consultation handoffs, and sustainable economics. For Korean hospitals, the strongest case for investment is a functioning pathway that can be measured and maintained.
FAQ
What should a hospital request before evaluating a prospective partner?
Request a description of the eligible audience, available communication channels, proposed referral workflow, payment responsibilities, and account-management resources. Audience size alone is insufficient to assess commercial fit.
How can a hospital pilot a partnership when referral volume is unknown?
Define a limited service scope, named coordinators, and an agreed review period. Record patient progression and staff time from the outset, then assess whether the process works before expanding commitments.
How should referrals be attributed when a patient also sees hospital advertising?
Record the institutional referral and ask the patient how they first discovered the hospital. Distinguish initial discovery from the contact that prompted consultation, rather than automatically assigning all value to the last interaction.
Should employers receive employees’ consultation details?
Benefit administration does not itself establish a basis for sharing clinical information. Review the applicable legal requirements and the specific arrangement, and consider whether administrative confirmation or aggregate reporting can meet the employer’s needs.
Sources
Related articles
Global Channels
Where Multilingual Patient Platforms Gain a Data Advantage
How multilingual patient platforms complement hospital CRM data and turn cross-market patient journeys into better acquisition and operating decisions.
Global Channels
Do Quote-Comparison Features Help or Hurt Hospital Profitability?
Quote comparison can build trust with international patients, but only when platforms explain scope, fit, and follow-up instead of flattening care into price.

Global Channels
Why Foreign Patient Landing Pages Win Through Evidence Sequencing, Not Translation Alone
Foreign patient landing pages convert when trust signals appear in the right order for each market, treatment category, and decision stage.