Cases & Data
What International Patient Reviews Leave Out: Language and Selection Bias
Why review language is a weak proxy for international demand, and how hospitals can separate patient experience from selection bias.
Public reviews offer international patients a visible account of care abroad. For hospital administrators, however, they represent a selected record of experience whose composition requires interpretation.
An English-heavy review profile does not establish that English-speaking patients dominate arrivals. Differences between language groups may reflect who visits, who receives a review request, and who ultimately publishes.
Review visibility reflects several selection stages
A published review depends on more than a patient having an experience. The patient must use the platform, feel able to write, decide to participate, and complete the publication process.
Language can influence each stage. A visitor may communicate comfortably with an interpreter yet hesitate to publish a detailed account. Another may regularly contribute reviews in a shared international language.
Platform familiarity also matters. Patients who rely on private communities or messaging groups may leave substantial feedback without contributing to the public platform the hospital monitors.
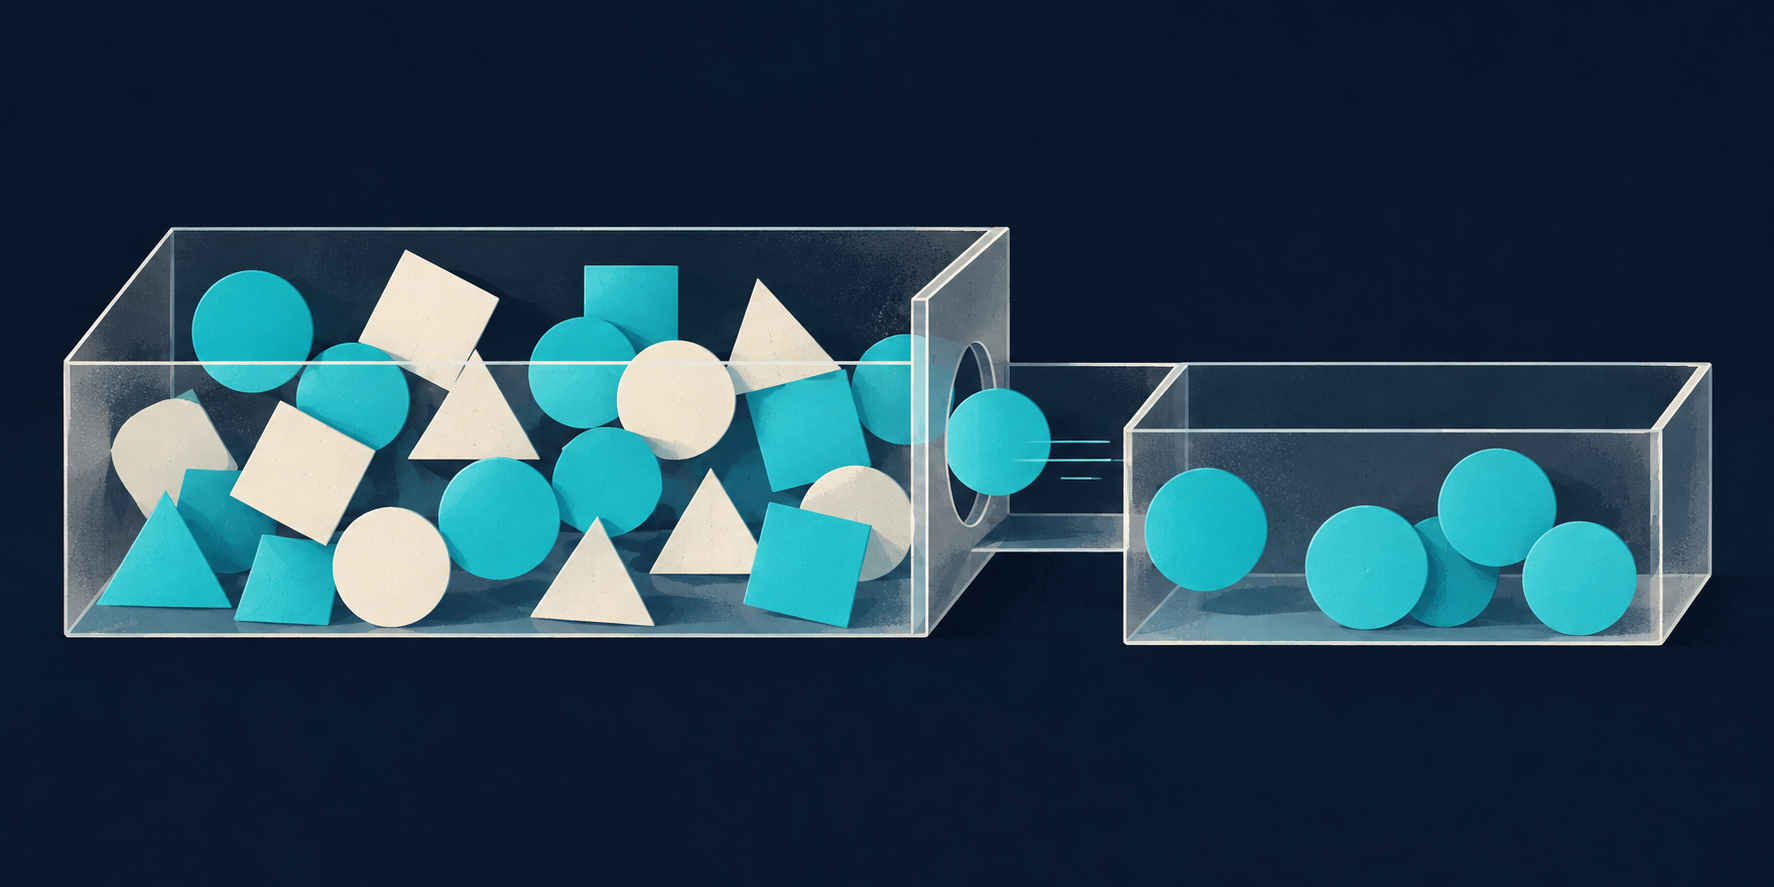
This creates a selection problem: the observable reviews may differ systematically from the population whose experience administrators want to understand. AAPOR’s standards and Pew Research Center’s methodological resources provide a useful foundation for examining participation and interpreting survey evidence.
Review volume therefore combines patient volume with participation behavior. More reviews in a language could mean more patients, a greater likelihood of receiving an invitation, a higher willingness to post, or some combination.
For a Korean clinic assessing international acquisition, the commercial implication is substantial. A visible language segment may appear to justify investment even when its prominence mainly reflects how feedback is collected.
Language, nationality, and residence answer different questions
Review language describes a communication choice. Nationality describes a citizenship attribute, while residence identifies where a patient lives. These variables overlap, but none reliably substitutes for the others.
An English-language review might come from a resident of Singapore, a Korean citizen living overseas, or an international resident already based in Seoul. Their acquisition journeys and travel requirements can differ considerably.
Residence may be more informative when examining travel logistics or local campaign reach. Preferred language is more useful for designing explanations and follow-up communication. Neither alone establishes the patient’s reason for choosing Korea.
Table: What each patient attribute can help explain
| Attribute | Useful analytical role | Interpretation to avoid |
|---|---|---|
| Review language | Language of publicly visible feedback | Treating it as a country identifier |
| Preferred communication language | Consultation and follow-up needs | Assuming it matches review language |
| Nationality | Citizenship-related segmentation where relevant | Treating it as current residence |
| Country of residence | Travel context and geographic acquisition analysis | Assuming everyone in a market shares a language |
Hospitals should collect only information relevant to a defined purpose and interpret missing fields explicitly. Guessing nationality from a name or assigning residence from review language introduces additional uncertainty.
This distinction also belongs in international patient acquisition analysis. Market demand should be assessed through inquiries, visits, and relevant patient attributes, with public reviews providing supporting context.
Apparent satisfaction gaps may reflect different experiences
Suppose reviews in one language are more positive than reviews in another. The immediate temptation is to describe a difference between national markets. That interpretation skips several competing explanations.
The groups may have received different procedures or service combinations. A dental consultation, a dermatology visit, and a surgical episode involve different expectations, costs, follow-up needs, and opportunities for assessment.
Evaluation timing can also change what a review captures. Feedback submitted immediately after a visit may describe reception and communication. Feedback submitted later may address recovery, ongoing support, or unresolved questions.
These are different observation points. Combining them into a language-level average can make differences in timing resemble differences in overall satisfaction.
The invitation process adds another layer. One language team may request feedback consistently, while another relies on individual coordinators. Requests delivered through different channels may reach different subsets of patients.
Before interpreting a group difference, compare patients with broadly comparable service contexts and feedback timing. Where records are limited, describe the observed difference without assigning its cause to nationality or culture.
Qualitative analysis should follow the same discipline. A recurring complaint about communication is operationally useful, but its frequency in public reviews does not establish how common it is among all visitors.
The denominator belongs in the patient record
The starting population should be the relevant patients who actually visited during a defined period. Reviewers are a subset of that population, not the denominator for measuring overall participation.
Hospitals then need to distinguish invitation from publication. A patient who was never asked and a patient who received a request but did not post represent different stages of the feedback process.
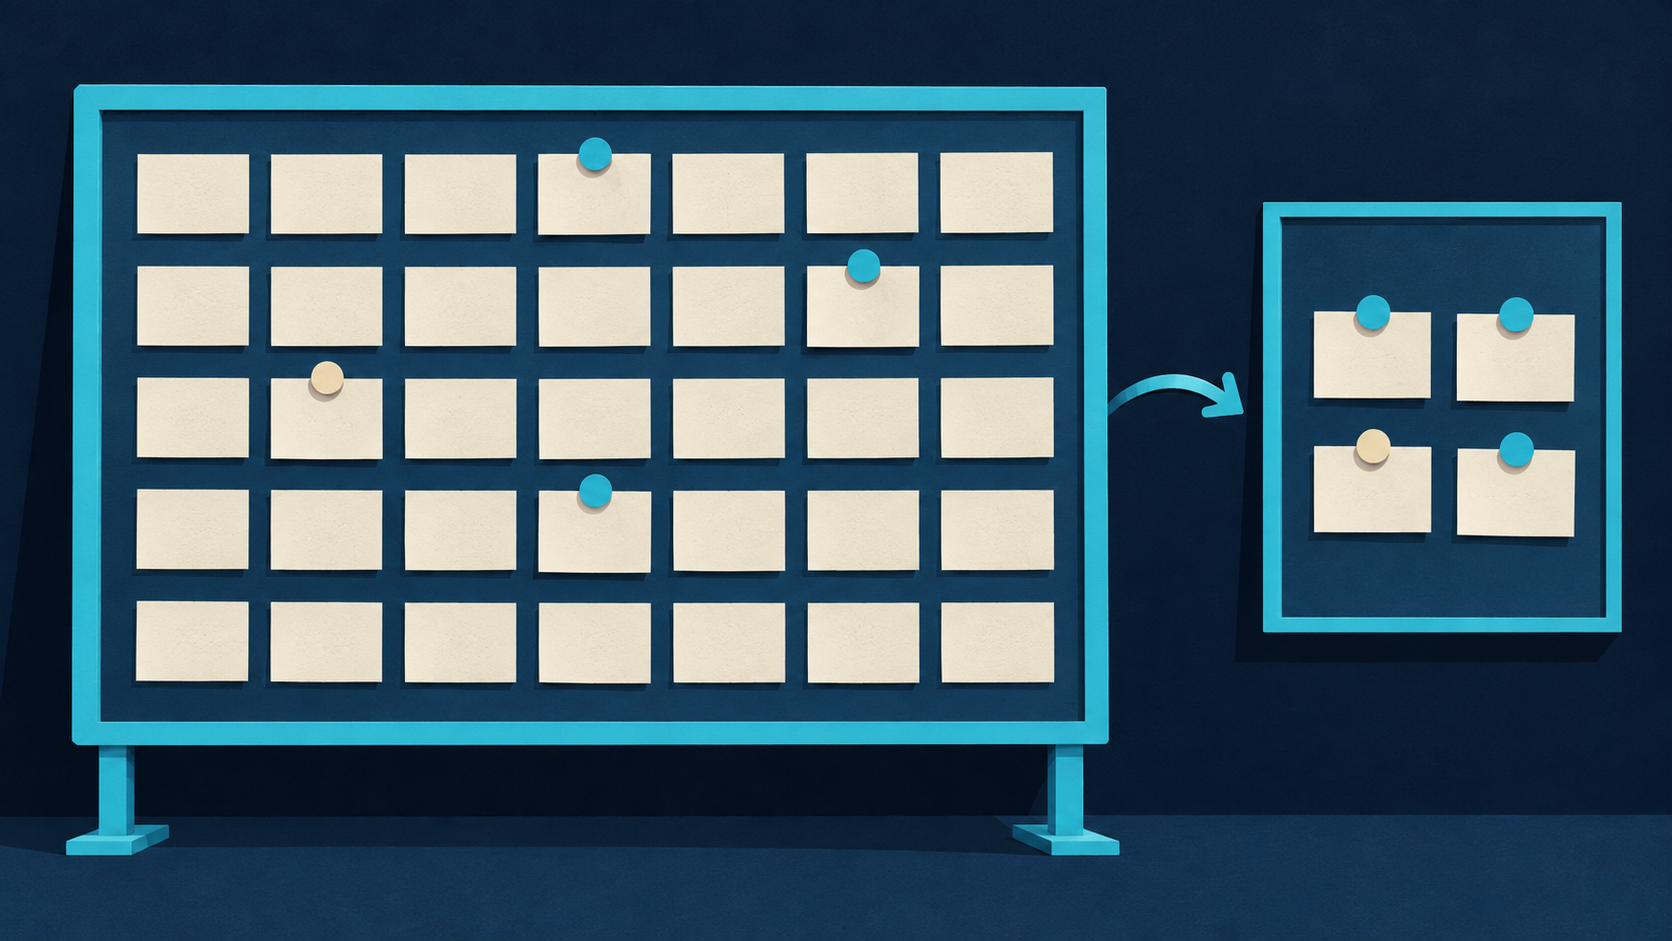
A practical record links the visit to whether a review request was sent, its language and timing, and whether publication can be reliably identified. Unmatched reviews should remain unmatched rather than being assigned through speculation.
Table: Locating selection within the review process
| Observation stage | Operational question | Potential source of distortion |
|---|---|---|
| Eligible visits | Which patient encounters belong in the analysis? | Inconsistent inclusion rules |
| Review invitations | Who received a request, and when? | Uneven coverage across teams or languages |
| Published reviews | Which invited patients are known to have posted? | Different willingness or ability to participate |
| Unlinked reviews | Which publications cannot be matched reliably? | Incomplete attribution |
| Internal feedback | Who responded through another channel? | Additional response selection |
This framework changes the management discussion. A low review count may indicate limited patient volume, weak invitation coverage, limited participation after invitation, or incomplete matching. Those explanations imply different operational responses.
For hospitals developing multilingual patient websites, the distinction also matters when presenting testimonials. Clearly contextualized accounts help readers understand the experience described without implying that the selection represents every international patient.
Review collection must also respect platform rules. Google Maps’ contribution policies are relevant to invitation practices, including incentives and selective solicitation. Improving measurement should not become an attempt to engineer a favorable public sample.
Internal feedback adds perspective, not a complete correction
Inviting non-reviewers to complete an internal survey can reveal experiences absent from public platforms. It does not automatically resolve selection bias: some invited patients will still decline or remain unreachable.
Pew Research Center’s methods resources underscore why recruitment, question wording, and collection mode deserve attention. AAPOR’s standards similarly support transparency about how evidence was obtained and what its limitations are.
Hospitals should therefore compare public reviews, internal responses, and operational records as distinct evidence streams. Agreement can strengthen an interpretation; disagreement can reveal differences in audience, timing, or willingness to speak publicly.
For example, positive public comments alongside internal reports of follow-up confusion warrant investigation. Neither source alone establishes the prevalence of the problem, but together they identify a specific part of the patient journey to examine.
The strategic value of international reviews lies in understanding what they reveal and how they became visible. When hospitals preserve the visit denominator, separate patient attributes, and document participation stages, reviews become more useful evidence for service improvement and market interpretation.
FAQ
Can we estimate country-level demand from review language?
Use review language as an exploratory signal, then validate it against inquiries and visits by country of residence. Multilingual patients and international residents make direct country attribution unreliable.
What should we do when a language group has very few reviews?
Describe individual themes and the limited coverage. Avoid ranking groups by average ratings when a small number of contributions could drive the apparent difference.
How should we handle reviews that cannot be linked to a patient visit?
Keep them in a separate, unlinked category. They can inform qualitative monitoring, but should not be included in a visit-based participation calculation without reliable attribution.
Should staff invite only patients who report a positive experience?
Use consistent, neutral invitation criteria and follow the platform’s policies. Selecting recipients according to expected sentiment distorts the evidence and may conflict with Google Maps’ contribution rules.
Does an anonymous internal survey eliminate response bias?
Anonymity may help patients share sensitive feedback, but participation remains voluntary. Report invitation coverage, response patterns, and collection timing alongside the findings.
Sources
Related articles
Cases & Data
When More International Patients Mean Less Profit: The Economics of Clinical Time
International patient growth improves hospital profit only when contribution, capacity limits, staffing thresholds, and channel costs are assessed together.
Cases & Data
Did Ads Bring New International Patients—or Capture Existing Demand?
Why attributed bookings do not prove patient growth, and how country-level experiments can reveal advertising’s additional contribution.
Cases & Data
Why Patient Residence Changes International Acquisition Results
Residence reveals the travel barriers hidden in international patient metrics—and changes how hospitals should interpret conversion, demand, and budgets.