Cases & Data
Why Standardized Multilingual Consultations Become a Platform Advantage
How multilingual inquiry data becomes a platform advantage through shared categories, contextual analysis, controlled access, and operational feedback.
A hospital platform can accumulate multilingual inquiries without becoming better at understanding international patients. Conversations become useful evidence only when teams can compare them while preserving what patients actually said.
For Korean clinics serving overseas markets, this distinction matters commercially. An inquiry about cost may reflect budget constraints, uncertainty about what a quotation includes, or an attempt to plan a trip. Recording each as the same signal can send marketing and consultation teams toward different conclusions.
Standardization needs both shared categories and original language
Standardization should create a common analytical layer while preserving the original consultation. A translated summary helps staff coordinate, but it can omit qualifications, uncertainty, or the sequence in which a patient raised concerns.
A useful record therefore connects the original message with a working translation and shared classification values. These layers serve different purposes: the original supports interpretation, the translation supports collaboration, and the categories support comparison.
Consider two inquiries classified as pricing questions. One patient asks whether an estimate includes follow-up appointments; another asks whether a lower-cost option is available. A shared category makes both discoverable, while the original wording explains why their next steps may differ.

HL7’s FHIR specification offers a relevant reference point for structured health information exchange. It does not provide a ready-made taxonomy for international patient acquisition. The narrower lesson is that reusable information depends on defined structures and consistent meanings, rather than free text alone.
Table: The complementary roles of consultation data layers
| Data layer | What it preserves | Analytical purpose |
|---|---|---|
| Original message | Patient wording and conversational context | Review an interpretation |
| Working translation | Meaning accessible to another team | Coordinate a response |
| Shared classification | Consistent categories across languages | Compare inquiry patterns |
| Classification history | Changes and their rationale | Explain revisions to reporting |
A platform loses interpretive depth if it keeps only categories. It loses comparability if it keeps only conversations. The value lies in maintaining a traceable relationship between them.
Country comparisons depend on how the audience is defined
“Country” is often treated as an obvious reporting dimension. In international healthcare, it may refer to nationality, current residence, campaign targeting, or the location from which an inquiry was submitted.
Those definitions are not interchangeable. A Japanese national living in Singapore who consults in English presents a different travel and communication context from a Japanese-speaking resident of Japan. Combining them may obscure the reason for a particular inquiry pattern.
Nationality, residence, and preferred consultation language should therefore remain separate fields, collected where relevant and appropriate. Missing information should remain identifiable rather than being inferred from a name, telephone prefix, or language choice.
Acquisition channel and treatment interest add another interpretive layer. A price-focused advertisement may attract different questions from an educational referral page. Dental and dermatology inquiries may also involve different planning considerations, even within the same residence market.
Before interpreting a country-level difference as a cultural preference, analysts should examine these contextual factors. Otherwise, a campaign’s message or a clinic’s service mix can be mistaken for a characteristic of an entire market.
This is where international patient acquisition operations connect with data design. The definitions used during intake determine whether later reporting can distinguish market demand from the effects of channel strategy and consultation practices.
Pricing questions describe a conversation, not a complete preference
The frequency of pricing questions is an observable behavior. Price sensitivity is an interpretation that requires additional evidence. Treating the former as a direct measure of the latter can distort decisions about messaging and service design.
An international patient may need a quotation to estimate travel costs, coordinate time away from work, or understand which services are included. Asking about price can therefore indicate progress toward a decision as well as concern about affordability.
The more useful unit of analysis is the consultation pathway. What happened after the patient received an explanation or estimate? Did they seek clarification, discuss appointment availability, postpone travel, or explicitly describe a budget constraint?
Table: Interpreting pricing questions through subsequent behavior
| Observed pattern | Plausible interpretation | Evidence to review |
|---|---|---|
| Asks about included services | Uncertainty about quotation scope | Follow-up clarification |
| Requests an estimate, then discusses dates | Active trip and appointment planning | Scheduling conversation |
| States a budget constraint | Potential affordability concern | Patient’s stated reason |
| Stops responding after receiving an estimate | Unresolved reason for disengagement | Follow-up record and timing |
These interpretations remain hypotheses until supported by the conversation. Silence after a quotation should not automatically become a price objection: travel constraints, response delays, or competing priorities may also explain it.
Comparable reporting also requires consistent definitions of progress. Requesting an estimate, proposing a date, and receiving a confirmed appointment are different events. A platform that merges them into a single booking label makes its own funnel harder to interpret.
Platform advantage develops through an operational feedback loop
A large archive is an asset only if it improves decisions. The stronger platform advantage comes from a repeatable process: classify consultations, review patterns, change operations, and observe what happens in subsequent conversations.
For example, repeated questions about quotation scope may justify revising an explanation template. Repeated uncertainty about appointment confirmation may point to unclear status messages. These are operational hypotheses that teams can assess against later records.
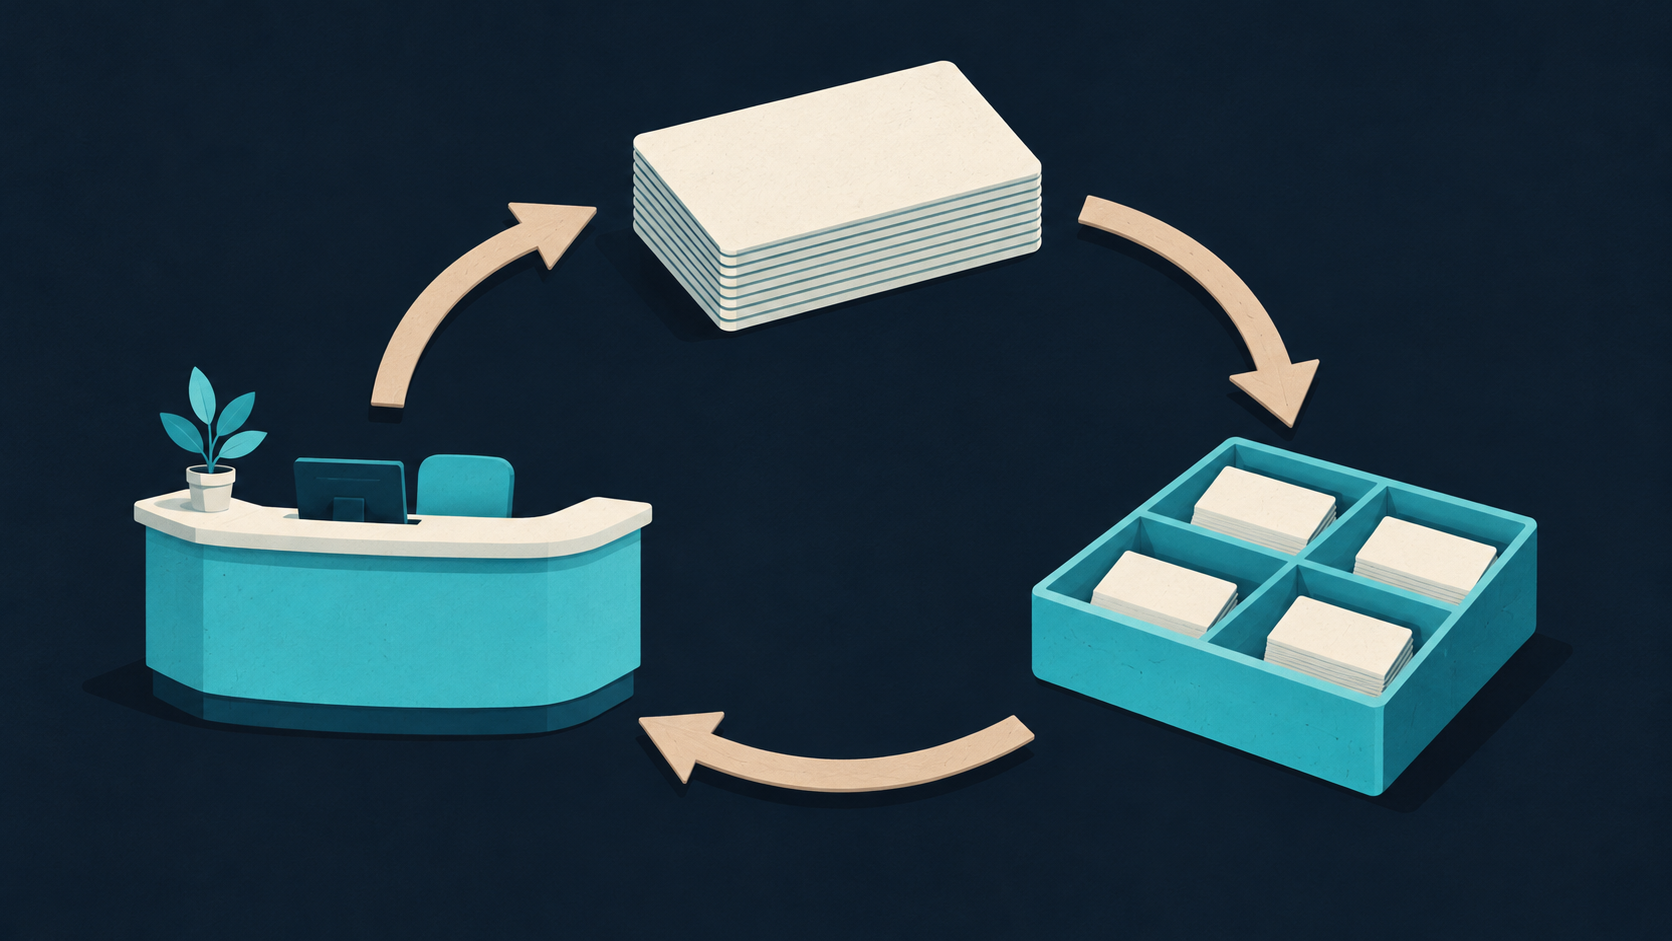
Classification rules need ownership and revision history. If staff broaden the meaning of “appointment intent,” the reported trend may change even when patient behavior does not. Recording when and why a definition changed helps prevent a reporting adjustment from being presented as commercial improvement.
The same discipline applies when correcting individual records. Teams should be able to distinguish the initial automated label, a reviewer’s correction, and the rule subsequently used for aggregation.
For a multilingual patient platform such as K-DIA, this creates a concrete test of data value: can a finding be traced into a service change and then evaluated? The advantage comes from that learning process, rather than record volume alone.
Access controls and uncertainty belong inside the analytical model
Consultation records may contain sensitive personal and health information. Access to original conversations and access to aggregate reporting should be treated as separate permissions, with each role receiving the information needed for its work.
A coordinator handling an active inquiry may need conversational detail. A marketer comparing acquisition channels may need grouped patterns. Aggregation still requires care, because narrowly defined combinations of residence, language, and treatment interest can make individuals recognizable.
The Personal Information Protection Commission’s guidance is an authoritative starting point for assessing Korean privacy obligations. Decisions about collection, access, retention, and disclosure require review against the applicable requirements and the platform’s actual operations.
Automated classification introduces a separate source of uncertainty. Mixed-language messages, indirect phrasing, and translation errors can produce misleading labels. Systems should allow an uncertain or unclassified state and route ambiguous cases for review rather than forcing every message into a confident category.
Small samples also limit interpretation. A pattern within a narrow segment may be temporary or reflect a particular campaign. WHO’s data resources provide a broader reference for disciplined use of health information; consultation analytics likewise needs explicit definitions and visible limitations.
Standardized multilingual consultations become a platform advantage when comparison remains connected to evidence. Preserving original meaning, separating audience attributes, interpreting complete pathways, and feeding reviewed findings into operations turns a conversation archive into a practical learning system.
常見問題
Can an existing spreadsheet support this approach?
Yes, provided it supports consistent field definitions, controlled access, and traceability to the source conversation. More specialized infrastructure becomes useful when permissions, revision history, or coordination become difficult to manage.
How should historical records be handled when categories change?
Keep the previous category definitions and document the transition. If older records are reclassified, identify that change in reporting so readers can distinguish revised measurement from changed patient behavior.
Who should resolve disagreements about a consultation label?
Assign an accountable classification owner and involve a reviewer with the relevant language competence. Record the reasoning so repeated disagreements can inform clearer category definitions.
Should every language use identical consultation scripts?
Shared analytical categories do not require identical scripts. Localize explanations for comprehension while keeping the underlying definitions of inquiry type, quotation status, and appointment progress consistent.
參考資料
相關文章
Cases & Data
What International Patient Reviews Leave Out: Language and Selection Bias
Why review language is a weak proxy for international demand, and how hospitals can separate patient experience from selection bias.
Cases & Data
When More International Patients Mean Less Profit: The Economics of Clinical Time
International patient growth improves hospital profit only when contribution, capacity limits, staffing thresholds, and channel costs are assessed together.
Cases & Data
Did Ads Bring New International Patients—or Capture Existing Demand?
Why attributed bookings do not prove patient growth, and how country-level experiments can reveal advertising’s additional contribution.