Patient Acquisition
Where Economies of Scale End in Shared Multilingual Patient Support
Shared multilingual support can improve staffing efficiency, but clinic-specific decisions determine whether pooled inquiries actually reduce total costs.
International patient inquiries rarely arrive in a steady stream. A Korean dermatology clinic may receive overseas messages while its domestic reception team is busiest; another clinic may have language staff available during the same period.
Pooling those inquiries can improve staff utilization. But the economic advantage depends on how much work a shared team can complete—and how much it sends back to each clinic.
For administrators evaluating a shared service, the central question is therefore operational: does pooling reduce the total effort required to resolve an inquiry, or simply relocate its first response?
Pooling creates value when demand patterns complement each other
A dedicated multilingual employee provides immediate capacity, but that capacity cannot be stored. Quiet periods at one clinic do little to relieve an overloaded employee at another unless the organizations share access to staff.
A shared team can absorb these differences. Its advantage is strongest when participating clinics experience demand at different times and staff have the language skills needed to serve the inquiries arriving then.
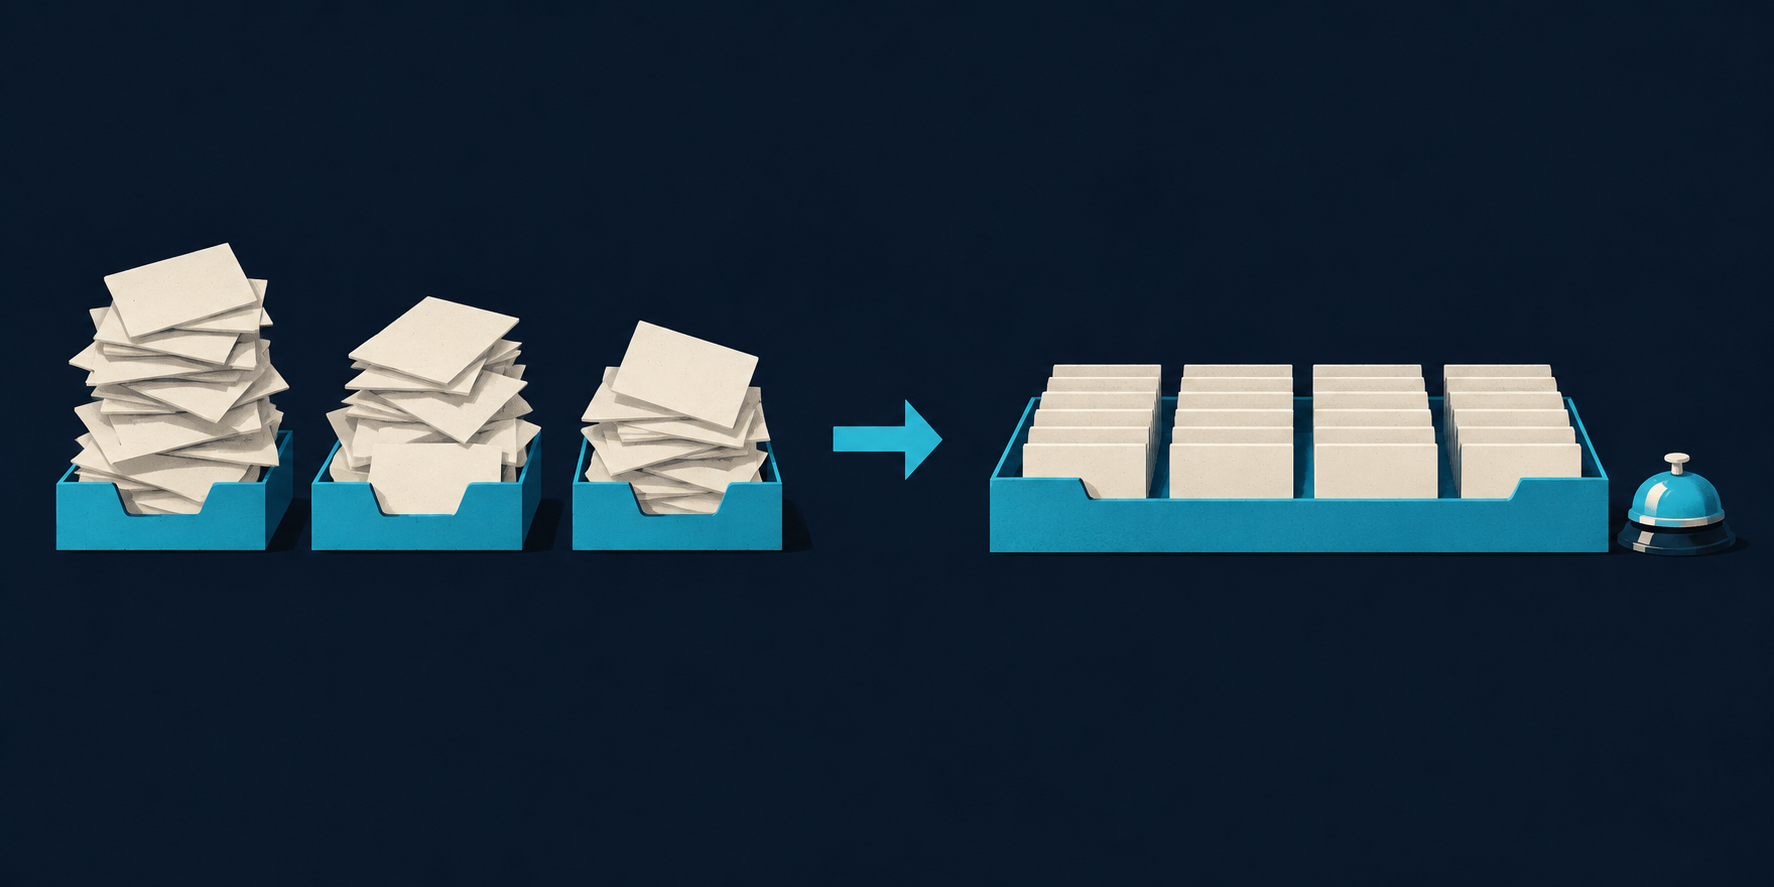
Clinic count is an unreliable proxy for this opportunity. Several clinics targeting the same country through similar campaigns may generate simultaneous peaks, leaving a shared team just as constrained as separate reception teams.
Time-zone diversity can help, but only when staffing hours match patient behavior. Combining inquiries from distant markets does not automatically create balanced workloads if everyone expects replies during the same narrow operating window.
Handling effort matters equally. A message requesting opening hours and an inquiry involving several procedures, travel dates, and medical records occupy very different amounts of staff attention.
The useful planning unit is therefore workload by language and time period, including follow-up effort. Raw message totals conceal the difference between brief exchanges and conversations that remain active across several shifts.
Standardization determines how much work stays shared
Pooling works most smoothly when the shared team can answer from current, clinic-approved information. Service availability, consultation procedures, location details, and document requirements are plausible candidates, provided their scope is clear.
The model becomes more demanding when patients ask for individualized prices, schedule commitments, or treatment suitability. These questions may require clinic-specific information or decisions that reception staff cannot independently make.
A shared team serving Korean plastic surgery, dermatology, and dental providers therefore needs more than multilingual fluency. It needs a reliable way to identify which information applies to which clinic and when that information requires verification.
Table: How inquiry characteristics affect the value of pooling
| Inquiry characteristic | Potential pooling benefit | Main constraint |
|---|---|---|
| Routine administrative question | Reusable answers reduce repeated work | Information must remain current |
| Request for published pricing | Shared staff can explain approved terms | Inclusions and conditions may differ |
| Appointment request | Common intake can simplify collection | Clinic capacity must be confirmed |
| Individual treatment question | Shared staff can route relevant information | Clinical assessment remains necessary |
| Unusual commercial request | Central intake can document the request | An authorized clinic decision is required |
For international patient acquisition operations, this distinction shapes the operating model. Centralizing initial contact creates value only when the path from inquiry to an authorized answer is also designed.
Standardization should make legitimate differences visible. Forcing every clinic into identical answers can create corrections later, particularly when prices, consultation arrangements, or appointment conditions differ.
Decision authority is the boundary of scale
The shared team’s authority should be explicit before patient conversations begin. Access to a clinic’s information does not necessarily include permission to negotiate a price, hold an appointment, or interpret clinical records.
Approved information can usually be communicated within defined conditions. Exceptions need a named decision owner, appointment confirmation needs an authoritative scheduling process, and clinical judgment belongs with the appropriate clinical professional.

These boundaries also affect response speed. When staff know who can decide, they can route a request directly; when authority is ambiguous, a conversation may circulate between reception, marketing, coordinators, and clinicians.
Table: Decision rights in a shared support model
| Decision area | Shared team’s role | Clinic responsibility |
|---|---|---|
| Approved information | Communicate current, authorized content | Maintain and approve the information |
| Commercial exception | Capture the request and explain the next step | Approve or decline through a designated owner |
| Appointment confirmation | Collect preferences and communicate verified status | Confirm availability under clinic rules |
| Clinical judgment | Route questions and relevant records appropriately | Assess through qualified clinical staff |
WHO’s patient-safety framing supports treating communication and organizational processes as safety concerns. It does not establish the economics of shared reception, but it explains why efficiency decisions must account for communication quality.
AHRQ’s TeamSTEPPS framework offers a complementary reference for teamwork and structured communication. Applied to this setting, its relevance is the discipline of clear handoffs and shared understanding, rather than a promise that centralization itself improves performance.
Measure the cost of resolution, including work returned to clinics
A lower shared-service staffing bill can coexist with higher clinic workloads. Reception may answer more messages centrally while clinic employees spend additional time correcting expectations, reconstructing conversations, or seeking missing details.
The meaningful cost boundary extends through inquiry resolution. That includes shared staffing, clinic review, translation clarification, repeated contact, and the effort needed to complete handoffs.
Approval delays deserve separate attention. Waiting does not always consume continuous staff time, but it can generate status requests, repeated explanations, and renewed checks when appointment availability changes.
Organizations should also define what counts as resolved. Sending a message is an activity; providing an authorized answer, confirming an appointment, or communicating a clear next step is an operational result.
Comparisons should distinguish inquiry types and languages. Otherwise, a team receiving more complex cases may appear inefficient, while another appears productive because it handles brief administrative exchanges.
This is where MSO consulting and operating-model design becomes relevant: staffing decisions must be assessed alongside approval structures, scheduling ownership, and the clinic work that centralization creates.
Expansion should follow evidence of manageable coordination
A practical evaluation begins with a defined scope of languages, clinic services, and decision rights. The purpose is to observe whether shared capacity absorbs demand variation without creating disproportionate downstream work.
Track where conversations leave the shared team, why they leave, and what information the receiving clinic needs. Repeated handoffs around the same issue may indicate unclear authority, outdated information, or an unsuitable division of work.
Expansion becomes more defensible when resolution effort remains manageable as clinics are added. If every additional clinic introduces extensive exceptions and separate approval routines, the service may be accumulating complexity faster than staffing efficiency.
The resulting model may remain partly centralized. Shared language coverage and administrative intake can coexist with clinic-owned scheduling decisions and specialist coordinators for complex cases.
Shared multilingual support reaches its economic limit where the savings from pooled capacity are overtaken by coordination effort. For Korean providers competing for international patients, the strongest model is the one that resolves inquiries with clear authority, reliable communication, and a visible total cost.
常见问题
What should clinics request before comparing shared-support proposals?
Request a precise scope of coverage, language availability, escalation responsibilities, reporting definitions, and charges for work outside the standard service. Proposals are difficult to compare when one includes follow-up and another covers only initial replies.
How should a shared team handle a patient asking for an immediate price exception?
Document the request, route it to the clinic’s designated commercial decision-maker, and explain when the patient can expect an update. Staff should communicate only terms they are authorized to offer.
Can an existing multilingual employee work alongside a shared team?
Yes. The clinic employee can retain responsibility for complex coordination while the shared team covers defined administrative inquiries or agreed coverage periods. Ownership of each conversation should remain clear.
What happens when a conversation spans several staff shifts?
The handoff should preserve the patient’s request, verified information already provided, outstanding decisions, and the next responsible person. Requiring patients or clinic staff to reconstruct the exchange adds avoidable work.
参考资料
相关文章
Patient Acquisition
How Local-Language Medical Content Changes the Patient Negotiation
Local-language content can shift international patient conversations beyond price. Its value depends on clearer choices, appropriate care, and measurable effects.

Patient Acquisition
Why Refund Terms Can Matter More Than Price to International Patients
Refund clarity helps international patients judge booking risk, clinic responsiveness, and the reliability of a medical journey to Korea.
Patient Acquisition
When Doctor Involvement Changes International Patient Conversion
A strategic look at why selective doctor involvement, not faster replies alone, can improve trust and conversion in international patient acquisition.